
 English
 Spanish
 Arabic
 Chinese
 French
Abdominal contouring · Patient selection guide
SkinTight™ Abs Tight may be considered for selected adults with mild to moderate abdominal skin laxity, but suitability cannot be decided from the word “loose” or from a photograph alone. A visible fold, lower-abdominal fullness or midline bulge may arise from the skin envelope, superficial fat, scar tissue, the abdominal wall or structures inside the abdomen. Clinical assessment must identify the main cause before any treatment is proposed.
The essential distinction
Not every abdominal bulge is loose skin. Superficial laxity and rectus diastasis are different anatomical problems: one affects the skin and subcutaneous envelope, while the other involves widening and reduced tension of the midline connective tissue between the rectus muscles. A hernia, visceral fullness, marked fat excess, fibrosis or a substantial hanging skin fold requires another discussion. SkinTight™ cannot repair the abdominal wall or substitute for skin-removal surgery.
The clinical starting point: what is actually causing the change?
At Dr Ducu Clinics, we offer Abs Tight as a minimally invasive body-contouring procedure for selected patients with mild to moderate abdominal skin laxity. Under local anaesthetic, a specialised cannula delivers controlled thermal energy beneath the skin. The intended response is tissue contraction and gradual collagen remodelling; we may also address small areas of superficial fat where this is clinically appropriate.
That treatment plane is important. It is beneath the skin, not inside the abdominal cavity and not within the fibrous midline that connects the abdominal muscles. The procedure may therefore be relevant to a suitable superficial tissue concern, but it does not close a hernia, repair rectus diastasis, remove visceral fat or excise a large skin apron.
Published reviews of radiofrequency-based skin tightening report possible improvements in laxity, but devices, treatment areas and outcome measures vary considerably. These findings support a cautious discussion of potential improvement; they do not establish a universal result, an exact percentage of tightening or equivalence to surgery.
Six different causes can look like the same abdominal concern
A person may use the same word—“looseness”, “pouch” or “bulge”—for findings that belong to different tissue layers. The comparison below is educational, not a self-diagnosis tool.
| Finding to distinguish | What it may involve | Relevance to Abs Tight |
|---|---|---|
| Superficial skin laxity | Reduced recoil, fine folding or mobile skin within the cutaneous and subcutaneous envelope. | Mild to moderate laxity may be considered, with a modest and variable degree of change. |
| Superficial fat | A pinchable deposit beneath the skin that contributes to local contour. | A small selected area may be addressed, but this is not weight loss or a substitute for extensive liposuction. |
| Rectus diastasis | Widening and attenuation of the linea alba, sometimes producing a midline ridge or dynamic bulge. | Subdermal heating cannot tighten or reconstruct the linea alba. |
| Hernia | A defect through which tissue can protrude, sometimes with pain, tenderness or a changing lump. | This requires medical assessment and is not treated by cosmetic radiofrequency. |
| Fibrosis or scar tethering | Firm, adherent or irregular tissue after surgery, trauma or another procedure. | It changes tissue movement and procedural risk; a separate diagnosis and plan may be needed. |
| Marked skin excess | A substantial fold or hanging apron, often after major weight change or pregnancy. | Energy treatment cannot remove the redundant skin; surgical excision is a different option. |
The abdomen can contain more than one finding at the same time. For example, mild surface laxity may coexist with diastasis and a small fat deposit. Treating one layer does not automatically correct the others, so the intended contribution of each proposed procedure should be stated separately.
Features that may support suitability
No single feature confirms suitability. The following factors may support a discussion when they occur together and when the person is medically suitable for an elective procedure.
Matched concern
Mild to moderate laxity
The main concern is superficial skin looseness that can plausibly be reached by the proposed treatment plane.
Stable context
Relatively stable weight
Large or continuing weight changes can alter the skin envelope and make both planning and result assessment less reliable.
Tissue safety
Healthy treatment area
There is no active infection, open wound, uncontrolled inflammation or other local finding that makes treatment inappropriate.
Proportionate goal
Realistic expectations
The person understands that improvement may be gradual and limited, and that untreated causes of fullness or bulging will remain.
The ability to follow our aftercare instructions, attend reviews and contact our clinical team if recovery changes also matters. A person seeking removal of a large skin fold, correction of muscular separation or substantial fat reduction is not made suitable merely by accepting a smaller procedure.
Treatment may need to be delayed or avoided during pregnancy or breastfeeding, with active infection or inflammation, open wounds, impaired healing, uncontrolled medical conditions, relevant allergies or other factors identified during the medical assessment. The treating clinician’s evaluation takes priority over any general checklist.
Assessment after pregnancy or a major weight change
Post-pregnancy abdominal change is not one diagnosis. Skin stretching may coexist with rectus diastasis, a hernia, altered fat distribution, stretch marks, a Caesarean scar and changes in pelvic-floor or abdominal-wall function. Similarly, after substantial weight loss, the dominant issue may be redundant skin rather than mild loss of firmness.
Skin envelope
Laxity and excess
The examiner considers elasticity, mobility, thickness, folds and whether there is too much skin for a non-excisional approach.
Abdominal wall
Diastasis or hernia
Standing, lying and dynamic examination can help distinguish a superficial concern from an abdominal-wall problem.
Timing
A settled baseline
Pregnancy, breastfeeding, hormonal change and weight fluctuation should be discussed because the tissues and treatment goal may still be changing.
There is no responsible universal waiting period that can be prescribed in a blog. Timing depends on recovery, health, breastfeeding, weight stability, future pregnancy plans and the proposed intervention. A future pregnancy can stretch the abdominal tissues again; this does not create a moral or cosmetic requirement to postpone treatment, but it is relevant to informed planning.
Previous surgery, liposuction and fibrosis change the assessment
A Caesarean section, abdominal operation, liposuction or previous energy-based treatment does not automatically rule out another procedure. It does mean that scars, altered sensation, tethering, uneven fat thickness and fibrosis must be mapped rather than treated as ordinary laxity.
Fibrotic tissue can feel firm, bound down or nodular and may restrict the movement of a cannula. A contour irregularity can also result from unequal fat thickness, scar adherence, swelling or an abdominal-wall issue. Applying heat without identifying the cause may fail to address the concern and may add risk.
Bring the dates and details of prior procedures, any operative or treatment records available, implant information where relevant, photographs of the recovery and a list of previous complications. After examining the area, we may recommend waiting, obtaining further records, using imaging for a specific question or choosing a different pathway.
What a clinical assessment should establish
Most distinctions begin with a medical history and physical examination. Reviews of rectus diastasis report that history and examination identify many cases, while ultrasound, CT or MRI may be used selectively to define the separation, assess muscle quality or investigate a coexisting hernia. Imaging is not a routine requirement for every cosmetic consultation.
| Assessment area | What is considered | Why it changes the plan |
|---|---|---|
| History and timing | Pregnancies, weight trajectory, symptoms, operations, treatments, healing and future plans. | Establishes whether the tissue state is stable and whether another diagnosis needs priority. |
| Surface and pinch examination | Skin recoil, thickness, mobility, superficial fat, scars, sensation and asymmetry. | Defines whether the accessible layer corresponds to the requested change. |
| Dynamic abdominal-wall examination | Contour at rest and with movement, midline doming, focal lumps, tenderness and functional symptoms. | Can identify features inconsistent with isolated skin laxity and prompt referral or investigation. |
| Health and medicines | Medical conditions, allergies, smoking or nicotine exposure, medicines and previous anaesthetic issues. | May affect bleeding, infection, healing, anaesthesia and whether elective treatment is appropriate. |
| Goal and acceptable trade-off | The exact area, desired scale of change, scars, recovery tolerance and attitude to uncertainty. | Prevents a limited procedure from being presented as the answer to a larger anatomical problem. |
The result of assessment may be a tailored Abs Tight plan, a modified treatment area, further medical evaluation, discussion of another procedure or a recommendation not to proceed. Declining treatment is a valid clinical outcome.
When another pathway may be more appropriate
The appropriate alternative is determined by the tissue or structure causing the concern, not by which procedure sounds less invasive.
Marked skin excess
Surgical skin removal discussion
Abdominoplasty can remove redundant skin and may include abdominal-wall repair, but it is major surgery with scars, longer recovery and a different risk profile.
Wall or fascial problem
Medical or surgical assessment
Suspected hernia, symptomatic diastasis or unexplained focal bulging requires assessment directed at the abdominal wall.
Different primary target
Fat or fibrosis pathway
Substantial fat, visceral fullness or post-procedural fibrosis should not be relabelled as simple skin laxity.
No compelling indication
No procedure
Observation remains appropriate when expected benefit is small, the anatomy does not match the treatment or the person does not want its risks and recovery.
The NHS describes abdominoplasty as surgery that can remove excess loose skin and fat and, in a full procedure, realign abdominal muscles. This explains why it can address anatomy that a subdermal energy treatment cannot—but it does not make surgery necessary or suitable for every person.
What suitability means for the procedure and recovery
For our Abs Tight procedure, we give an indicative treatment time of approximately two hours and use local anaesthetic. The planned zone, anatomy and any separately agreed treatment can affect the actual appointment. Being awake under local anaesthetic does not make the procedure pain-free or risk-free.
| Stage | What should happen | Decision boundary |
|---|---|---|
| Consultation | The concern, tissue layer, health, alternatives, material risks and expected scale of change are discussed. | Consultation does not commit the person to treatment. |
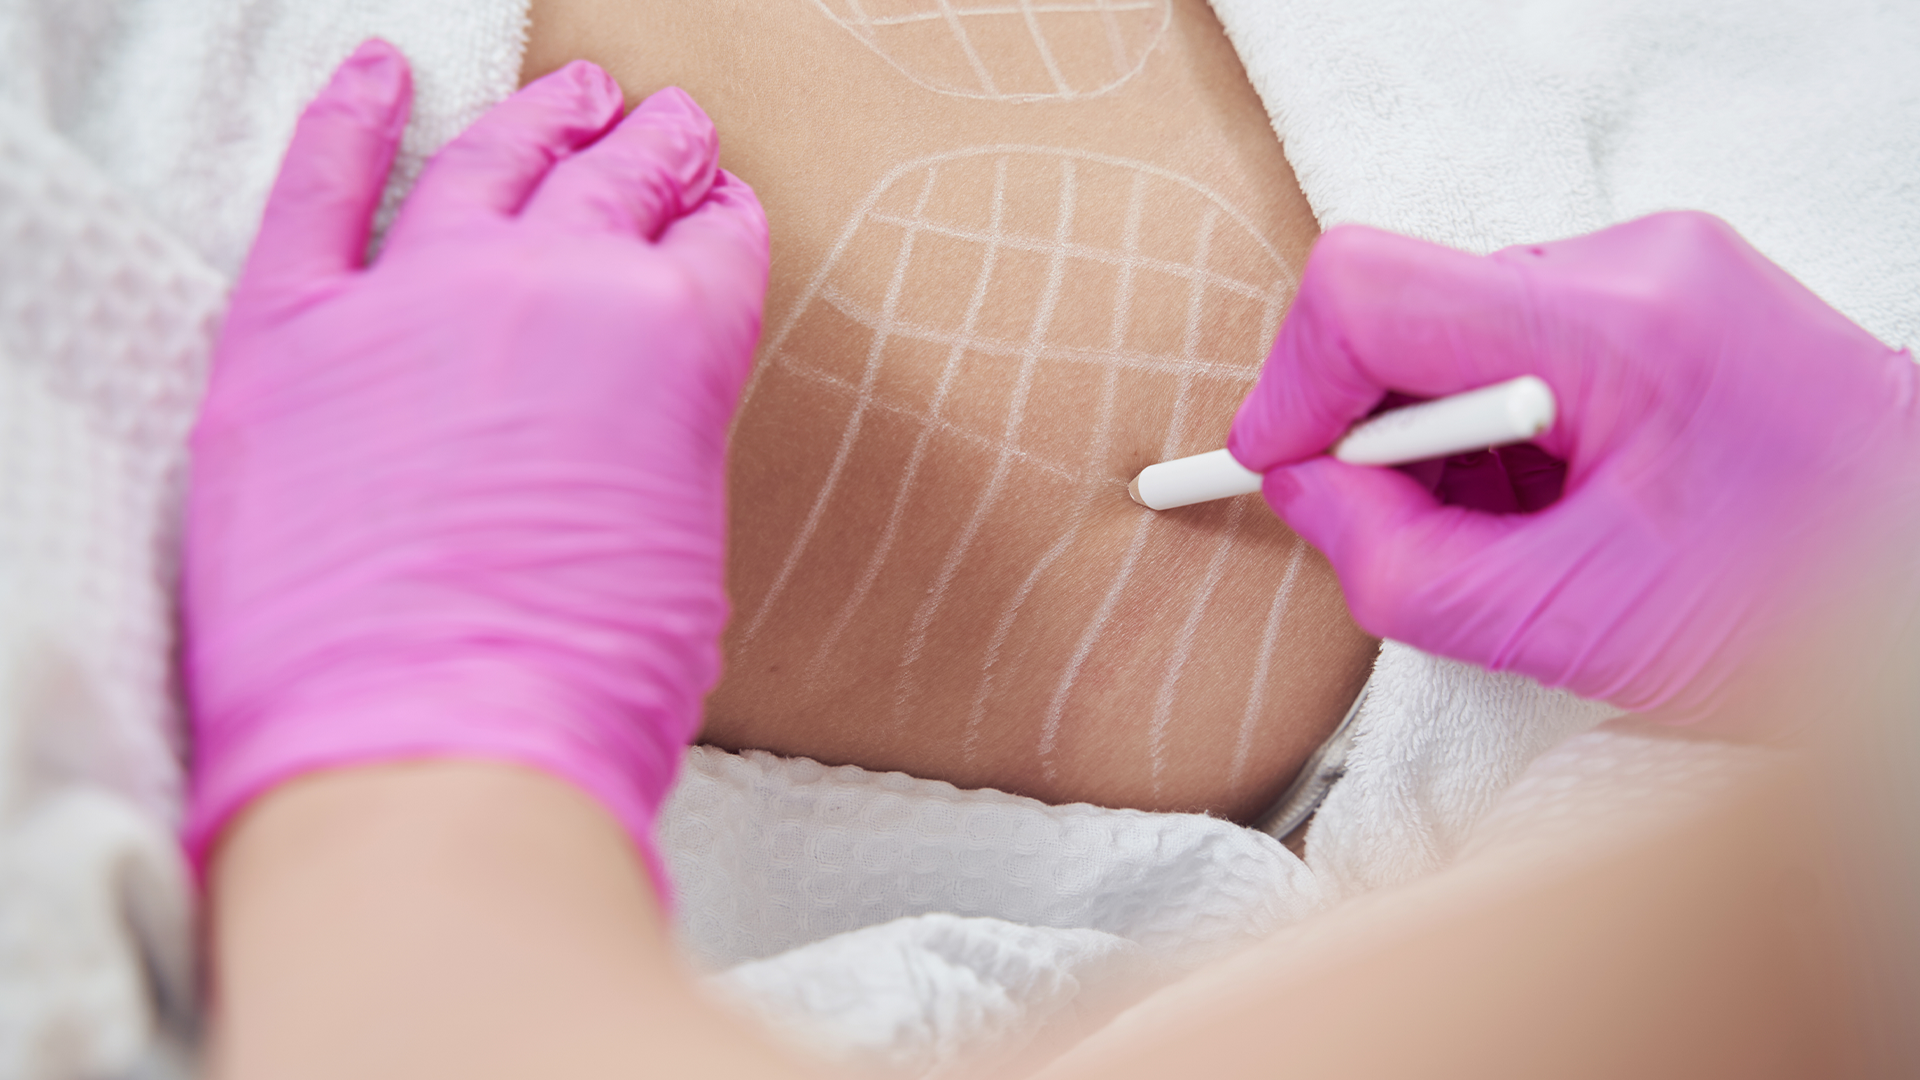
| Treatment mapping | The intended superficial zones and areas to avoid are marked before local anaesthetic and cannula treatment. | Diastasis, hernia and internal fullness are not treatment zones. |
| Early recovery | Swelling, bruising, redness, tenderness and temporary altered sensation may occur; compression may be advised. | Recovery varies, and written instructions take priority over generic timelines. |
| Later review | Healing, contour, firmness and the original target are reviewed after swelling settles and remodelling progresses. | A modest or uneven result does not automatically mean that more treatment is appropriate. |
For selected patients, we may discuss PLLA, hyaluronic acid-based treatment or Morpheus8 as an additional or separate option, but none is an automatic component of Abs Tight. Each has a different target and requires its own indication, consent discussion and risk assessment.
No exact degree or duration of tightening can be promised. Skin quality, treatment extent, healing, age, weight change, pregnancy, smoking or nicotine exposure and the continuing behaviour of the tissues can all influence the outcome. Our article on how SkinTight™ Abs Tight is planned explains how the treatment area, energy delivery and any combined components are decided.
Risks, complications and warning signs
Potential effects and complications include pain or tenderness, swelling, redness, bruising, bleeding, infection, delayed healing, burns or other thermal injury, blistering, skin damage or necrosis, scarring, prolonged firmness, nodules, contour irregularity, asymmetry, pigmentation change, altered sensation, unwanted fat loss, an unsatisfactory result and the need for further treatment. Personal risks depend on health, anatomy, treatment extent and previous procedures.
The possibility of a medical abdominal problem must also remain separate from procedural risk. New or persistent abdominal pain, a focal bulge, vomiting, bowel symptoms or a lump that becomes hard or tender should not be assumed to be a cosmetic skin issue.
Seek prompt assessment for an unexpected or worsening change
After treatment with us, contact our clinical team promptly for severe or increasing pain, rapidly worsening or one-sided swelling, persistent bleeding, spreading redness, fever, pus, blistering, dark or pale skin, wound breakdown, marked sensory change or any symptom we have identified as urgent.
Call 999 for breathing difficulty, chest pain, collapse, signs of a severe allergic reaction or another life-threatening emergency. Sudden severe abdominal pain with vomiting or a hard, painful bulge also needs urgent medical assessment. NHS 111 can advise when urgent help is needed but the situation is not immediately life-threatening.
Prompt contact does not prove that a complication or hernia is present. It allows an appropriate professional to examine a potentially time-sensitive problem rather than relying on online descriptions or photographs.
Questions to ask at an Abs Tight consultation
GMC guidance requires doctors offering cosmetic interventions to discuss outcomes, benefits and risks clearly, obtain consent themselves and allow time for reflection. Useful questions include:
- What proportion of my concern is skin laxity, superficial fat, scar tissue or abdominal-wall anatomy?
- Is there any sign of rectus diastasis or a hernia that needs separate assessment?
- Which exact zones would be treated, and which findings would remain unchanged?
- How do previous surgery, liposuction, scarring or altered sensation affect my risk?
- What degree of improvement is realistic without removing skin?
- Who will perform the procedure, and what relevant training and experience do they have?
- What are the material risks for my health, tissue quality and proposed treatment map?
- What compression, activity restrictions, reviews and out-of-hours support are planned?
- What are the alternatives—including no treatment—and what happens if the change is modest or uneven?
Frequently asked questions
Could mild loose abdominal skin be suitable for Abs Tight?
How can skin laxity be distinguished from rectus diastasis?
Can Abs Tight repair rectus diastasis?
Can the treatment correct an abdominal hernia?
Can it remove a hanging fold of excess skin?
Is Abs Tight a weight-loss treatment or a substitute for liposuction?
May Abs Tight be considered after pregnancy?
What if another pregnancy is planned?
Does a Caesarean scar make someone unsuitable?
What if I have had abdominal liposuction?
Do stretch marks rule out treatment?
Does weight need to be stable first?
Is ultrasound or another scan always required?
Are Morpheus8, PLLA or hyaluronic acid automatically included?
What may make treatment unsuitable or inappropriate for now?
Individual assessment
Identify the tissue layer before choosing a contouring treatment
A consultation can distinguish superficial laxity from fat, fibrosis, rectus diastasis, hernia or marked skin excess, then explain realistic options, limitations, recovery and risks without committing you to treatment.
Medical and regulatory sources consulted
- Dr Ducu Clinics: Abs Tight – Abdominal Skin Tightening Treatment
- Superficial Abdominal Skin Laxity Versus Rectus Diastasis: Distinct Pathophysiological Entities
- Diagnostic techniques for diastasis recti: a systematic review
- The Radiology of Abdominal Wall Repair: Rectus Diastasis and Hernias
- Endodermal radiofrequency for skin tightening and contour improvement: systematic review
- A Systematic Review of Subsurface Radiofrequency Treatments in Plastic Surgery
- NHS: Tummy tuck (abdominoplasty)
- NHS: Choosing who will do your cosmetic procedure
- GMC: Guidance for doctors who offer cosmetic interventions
- ASA/CAP: Guidance on marketing cosmetic interventions